Denise van Hout, MD, PhD
Postdoctoral Researcher
Julius Center for Health Sciences and Primary Care
University Medical Center Utrecht, the Netherlands
Keywords
Adaptive platform trial, Regulatory efficiency, REMAP-CAP, Study design, Study startup.
Key Points
Randomised Embedded Multifactorial Adaptive Platform trial for Community-Acquired Pneumonia (REMAP-CAP) began in 2016 as a data driven analysis of ethical, administrative, and logistical and ethical (EARL) delays in clinical trials studying respiratory infections. The goal was embedded trials that are flexible, efficient, and agile to provide clinicians with high-quality evidence to make the best treatment decisions.
REMAP-CAP is a global multifactorial adaptive platform trial with a master protocol that can investigate multiple interventions in different treatment domains for a single disease.
Over 8000 patients in REMAP-CAP were randomized to 44 interventions in 16 different treatment domains between January 2019 and June 2023. Patients could be randomized to more than 1 domain resulting in 15656 randomizations. Enrollment increased during the COVID-19 pandemic.
Dr. van Hout believes that to improve clinical trials, we should treat the challenges as a scientific problem and solve them with the same rigor.
Regulatory requirements and informed consent regulations differed among sites causing confusion for the researchers about what documents should be submitted with the contract and protocol in each country. Drug labeling requirements in some countries also slowed protocol approval. EARL processes also slowed trial initiation and patient enrollment.
It was clear that overall enrollment in the UK outpaced the other 257 sites worldwide. The UK had a shorter period of time to a fully signed study contract and protocol approval compared with sites in other countries (5 days in the UK compared with 183 days in non-UK countries). This quicker time to signed contract was accomplished by either accepting the contract as-is or rejecting the contract – without negotiating small details. The UK was also 3 months faster than non-UK countries at enrolling the first patient after study approval (1 month vs 4 months, respectively) leading to more enrollment and more research questions answered.
In January of 2022 the EU centralized regulatory submission to a single portal (CTIS) to ease and speed the process of starting a new trial.
Discussion Themes
Adaptive platform trials were uncommon before the COVID-19 pandemic, but their value became clear during the pandemic. After the pandemic, REMAP-CAP focuses on different treatment domains for pneumonia. Maintaining the infrastructure for an adaptive platform trial is difficult if there is not a clear need such as there was during the COVID-19 pandemic.
Centralizing approval for trials under one government body could speed the approval process for studies. During times of high need, prioritizing one or two good trials over a lot of smaller trials can also help speed the process.
The NIH Pragmatic Trials Collaboratory Implementation Science Core, led by Devon Check and Hayden Bosworth, has developed a new chapter on implementation to assist study teams with the complex process of using and studying implementation strategies to help implement research findings into clinical care. The chapter includes sections on:
Case studies are used to illustrate how pragmatic clinical trials embedded in healthcare systems use implementation frameworks, including examples from RAMP, BEST-ICU, STOP CRC, TSOS, ABATE, STEP-2, and GRACE.
Pragmatic clinical trials are conducted as part of routine healthcare delivery and often compare an intervention to usual care. To do this, researchers must understand, monitor, and document standard care at participating research sites.
At the NIH Pragmatic Trials Collaboratory’s 2025 Annual Steering Committee Meeting, Duke University’s Emily O’Brian asked a panel of trialists about the strategies they used to define and document usual care. The panelists included Rachel Winer, co–principal investigator (PI) of STEP-2;, Richard Platt, co-PI of INSPIRE; and Christine Goertz, co-PI of IMPACt-LBP.
Key Strategies
Establish a community of individuals who are interested in and committed to answering the research question
Develop relationships: visit each site and have monthly coaching calls
Get commitment in advance from sites to hold their practice constant for the duration of the trial
Have sites complete readiness surveys or feasibility assessments that include questions about potential upcoming quality improvement initiatives
Minimize burden on sites as much as possible
The Navigating the Unknown chapter of the Living Textbook includes descriptions of unanticipated challenges that may occur during the years-long course of a study that can have profound effects on usual care, including:
At the NIH Pragmatic Trials Collaboratory’s 2025 Annual Steering Committee Meeting, Angelo Volandes, co–principal investigator (PI) of the ACP PEACE trial, led a panel of investigators who shared key challenges and lessons learned from their recently launched trials. The panelists included Stephanie Fitzpatrick, PI of the MOMs Chat & Care Study, Elizabeth Wick, co-PI of I CAN Do Surgical ACP, and ChenChen Wang and Robert Saper, co-PIs of TAICHIKNEE.
MOMs Chat & Care Study
Goal: To test the effectiveness of Northwell Health’s MOMs navigation program at 2 levels of intensity designed to facilitate timely, appropriate care for high-risk Black and Latina birthing people and reduce risk for severe maternal morbidity
Key Challenge: Low recruitment
Solutions:
Expanded inclusion criteria to include Hispanic/Latina patients, those with lower risk factor scores, and gestational of less than 17 weeks instead of less than 13 weeks
Added manual review of charts to ensure the patients they telephoned for recruitment are pregnant and to determine the number of weeks of pregnancy
Changed recruitment materials and general approach so that empathy is at the forefront
Goal: To identify a systems-based approach to help older adults undergoing major elective surgery engage in advance care planning decisions
Key Challenge: One site will finish 6 months early but will still have access to the platform for research, which provides an opportunity they do not want to waste
Solution: Use the trial infrastructure to pilot test another intervention in the remaining months of trial time. The plan is to develop and test human-in-the-loop patient-facing generative AI to assess the quality of patient–AI interactions and answer additional questions, potentially laying the groundwork for future trials.
Goal: To determine whether remotely delivered tai chi is feasible across the 4 partnering healthcare systems and if tai chi, compared with routine care, will improve physical health (including knee pain and function), mental health, and healthcare utilization
Key Challenge: Long delays at institutional review board due to backlogs
Solution: The PI understood that many organizations had to cut costs and reduce IRB and regulatory staff, which likely drove delays in regulatory approval. When the study leadership interacted with the IRB, they did so in a generous and curious way, asking how they could help. The regulatory staff acknowledged the problem and suggested that, as the trial is federally funded and meets the regulatory criteria to be considered minimal risk, it should take priority.
Focusing on the trial’s intention is the first step in designing a trial that successfully answers its primary research question. For an introduction, read Promoting Both Internal and External Validity: Designing the Trial to Match Its Intention, which describes considerations for choosing a pragmatic or explanatory approach. While both approaches are valuable, their purposes are different and will lead to different design choices. As a result, designs that are more pragmatic will have conclusions and recommendations that are more useful for clinical or policy decision-making, and designs that are more explanatory will be more helpful in expanding scientific knowledge.
Case Study of Trial Design in a Renal Dialysis Setting
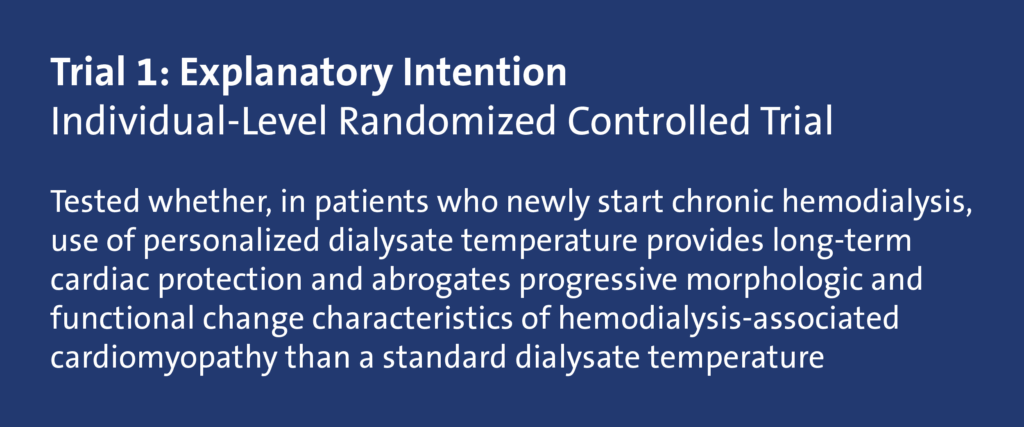
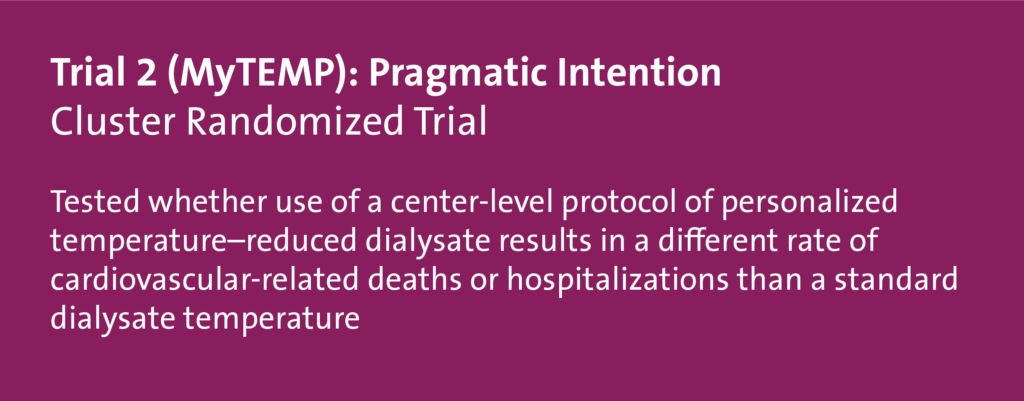
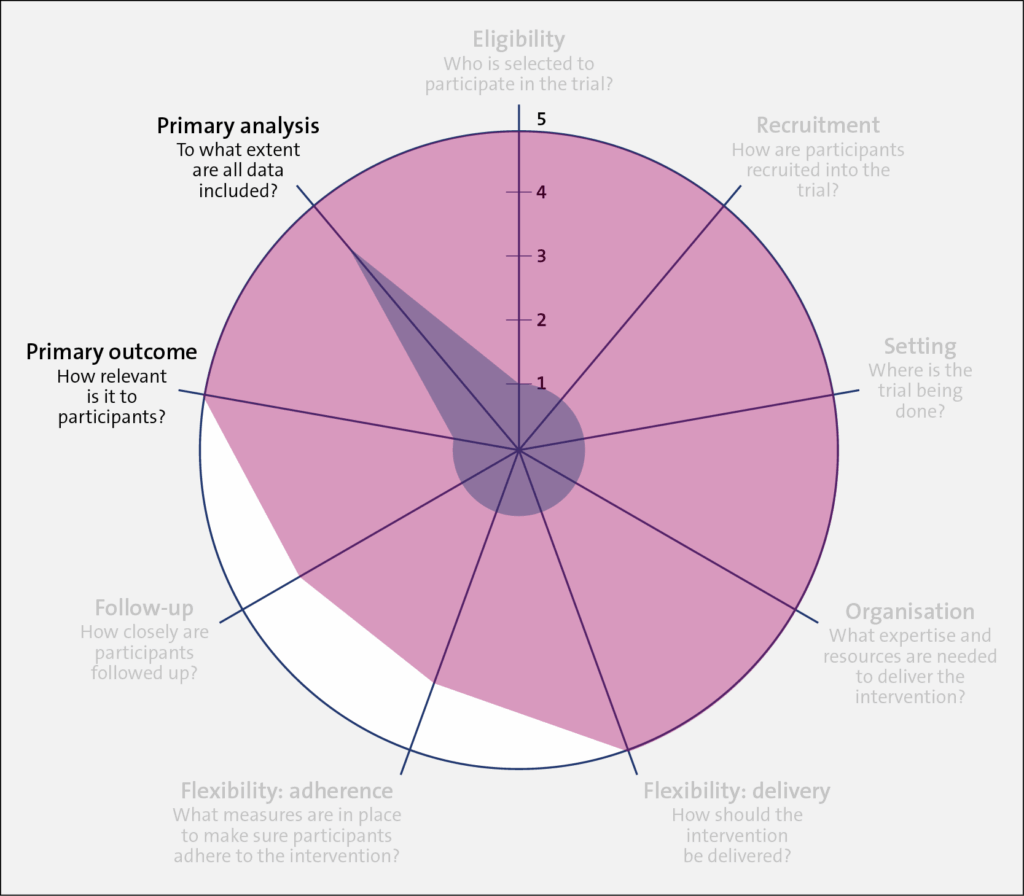
This case study illustrates the design of 2 randomized controlled trials that examined the temperature used in hemodialysis. Using the PRECIS-2 framework, we discuss insights about opportunities and constraints that a renal dialysis setting offers and show how the design of the trials aligned with their intention. Trial 1 was more explanatory in intention, to test a hypothesis about a mechanism of action: that personalizing dialysate temperature would reduce adverse changes in cardiac morphology and function compared with not personalizing the dialysate temperature (Odudu et al 2015). Trial 2 (the MyTEMP trial) was more pragmatic in intention, to help choose between 2 treatment policies by answering the question of whether patients in dialysis centres that personalized dialysate temperature would be better off in terms of cardiovascular death or hospitalization than patients in centers that maintained fixed temperatures (MyTEMP Writing Committee 2022).
We begin with some background on the 2 trials and the PRECIS-2 domains that will guide the step-by-step considerations for situating the trials on the pragmatic-explanatory continuum.
Trial 1 Characteristics (Shaded Blue)
Personalized dialysis temperature compared with 37° C (98.6° F)
Unit of randomization: individual patient
Patients in Nottingham, United Kingdom, enrolled from September 2009 through January 2013
1 year of follow-up
73 patients would have approximately 11,000 hemodialysis sessions during the trial
Individual-level consent
Trial-specific data collection
Primary outcome: change in the resting ejection fraction measured by cardiac magnetic resonance imaging (MRI) at 12 months compared with baseline
Cardiac structure, function, and aortic distensibility assessed by cardiac MRI
Trial 2 (MyTEMP) Characteristics (Shaded Red)
Personalized dialysis temperature compared with 36.5° C (97.7° F)
Unit of randomization: centers in Ontario followed from April 2017 to March 2021
Maximum 4 years of follow-up
84 centers, 15,413 patients (approximately 6000 entered at start of the trial, approximately 9400 entered during the trial)
Approximately 4 million hemodialysis sessions during the trial
Altered consent by patient notification via poster and newsletter, allowing opt-out by patients or providers
Baseline and follow-up data from large administrative databases
Primary outcome: a composite of cardiac death or hospital admission with myocardial infarction, stroke, or congestive heart failure
Evaluating the Trials Using PRECIS-2
For study teams, the broad steps of evaluating a trial using the PRECIS-2 wheel include:
Defining the trial’s intention
Aligning the design to the intention
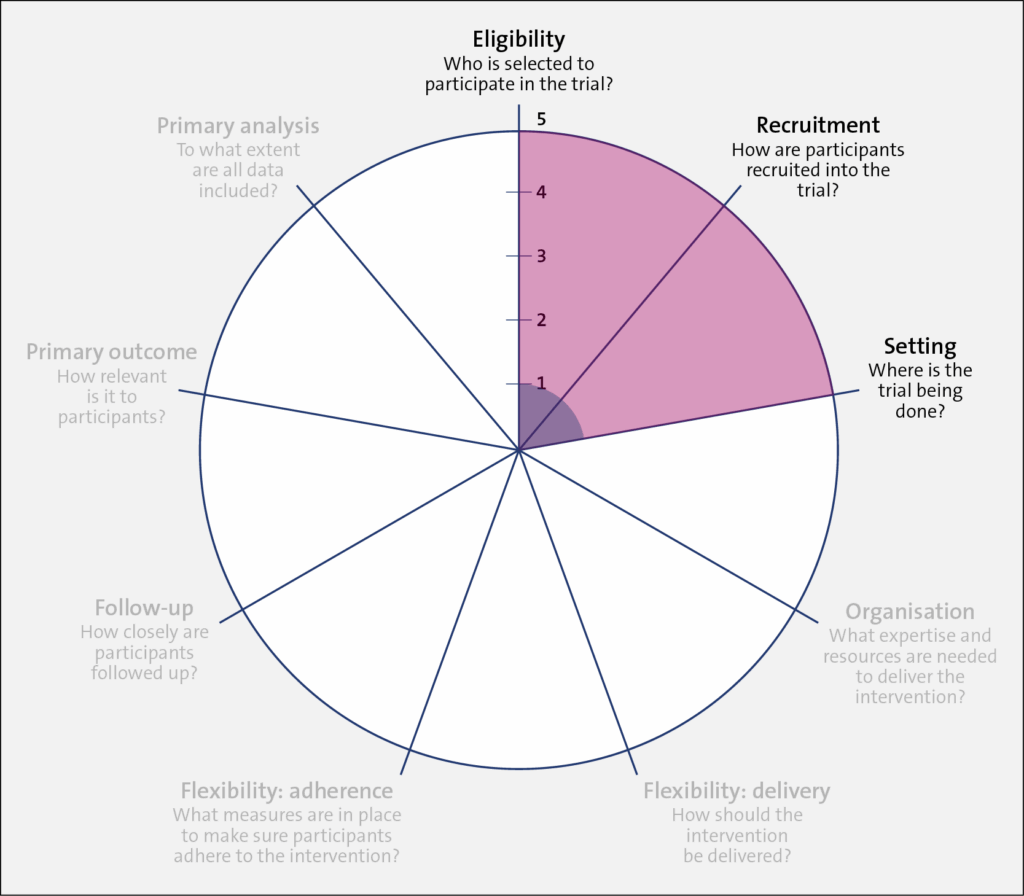
Identifying the trial’s location on the explanatory-pragmatic continuum (from 1 to 5) for each of the 9 domains (the spokes of the wheel)
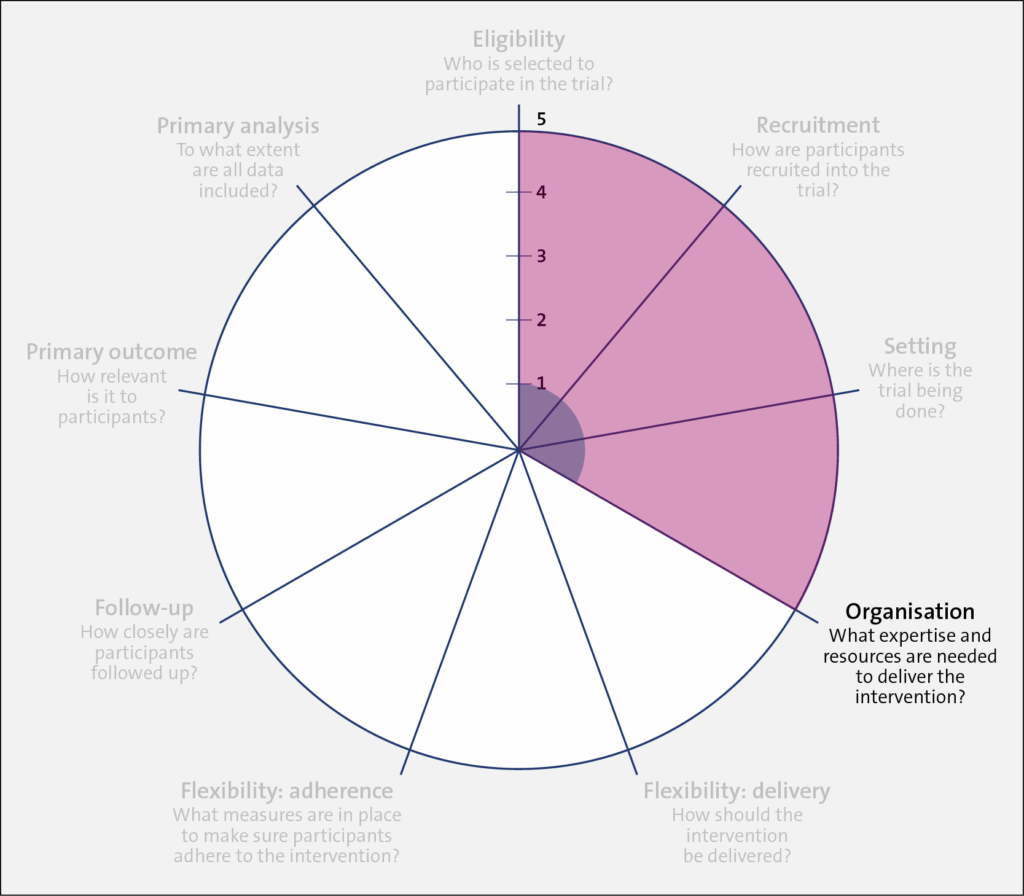
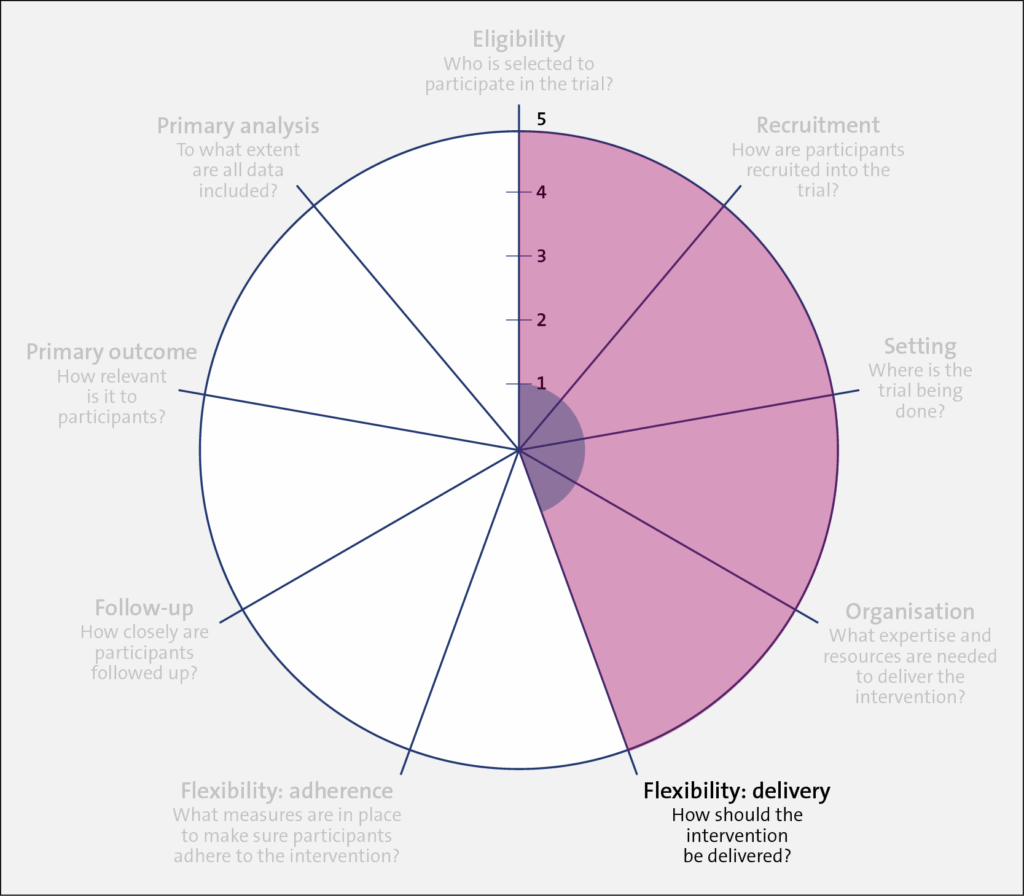
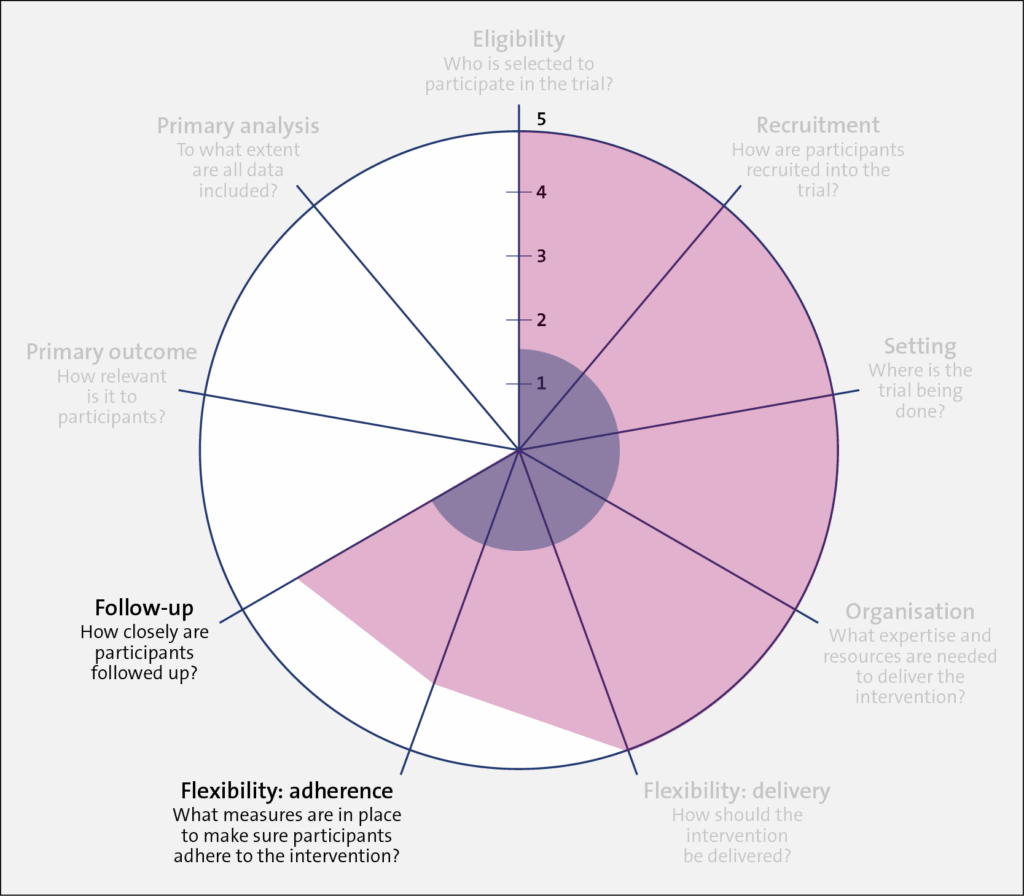
Once the intention of the trial is set (pragmatic or explanatory), the designer should align their design choices to their chosen intention across all 9 domains of the PRECIS-2, as outlined in the table below. In this brief discussion, we focus on one of these domains, eligibility, with some mention of the primary outcome.
A very explanatory design approach, with many exclusions and a more physiological outcome (morphology) rather than a patient-centered outcome (mortality), is represented closer to 1 on the PRECIS 2 wheel for each of the domains. Such exclusions may include trial participants who are not adherent to the intervention, who do not respond to treatment, who are at low risk for the primary outcome, and children or older patients. The trial also uses diagnostic tests that are not routine in usual care, to assess both patient eligibility and the primary outcome. On the other hand, a very pragmatic design approach with domains that are set to match as closely as possible those in usual care, that includes almost all patients with the diagnosis, that uses usual diagnostic tests to make the diagnosis, and that chooses outcomes that are directly relevant to patients is represented closer to 5 on the PRECIS-2 wheel.
PRECIS-2: Kirsty Loudon et al. BMJ 2015;350:bmj.h2147. Copyright 2015 by British Medical Journal Publishing Group. Used by permission.
The Table below summarizes the PRECIS-2 domains and the considerations for each domain.
Table. PRECIS-2 Domains and Considerations
PRECIS-2 Domain
Considerations
Eligibility
To what extent are the participants in the trial like those who would receive this intervention if it was part of usual care?
Recruitment
How much extra effort is made to recruit participants over and above what would be used in the usual care setting to engage with patients?
Setting
How different are the settings of the trial from the anticipated usual care setting?
Organization
How different are the resources, provider expertise, and the care delivery organization in the trial and those available in the anticipated usual care situation? Are extra resources added?
Flexibility: delivery
How different is trial flexibility of delivery from flexibility anticipated in usual care?
Flexibility: adherence
How different is trial flexibility in monitoring or encouraging adherence from the flexibility anticipated in usual care?
Follow-up
How intrusive is measurement and follow-up of participants in the trial vs anticipated follow-up in usual care?
Primary outcome
To what extent is the trial’s primary outcome directly relevant to participants?
Primary analysis
To what extent are all data included in the analysis of the primary outcome?
Next, we evaluate the characteristics of both trials and describe the considerations behind each of the 9 PRECIS-2 domains.
Domains: Eligibility, Recruitment, and Setting
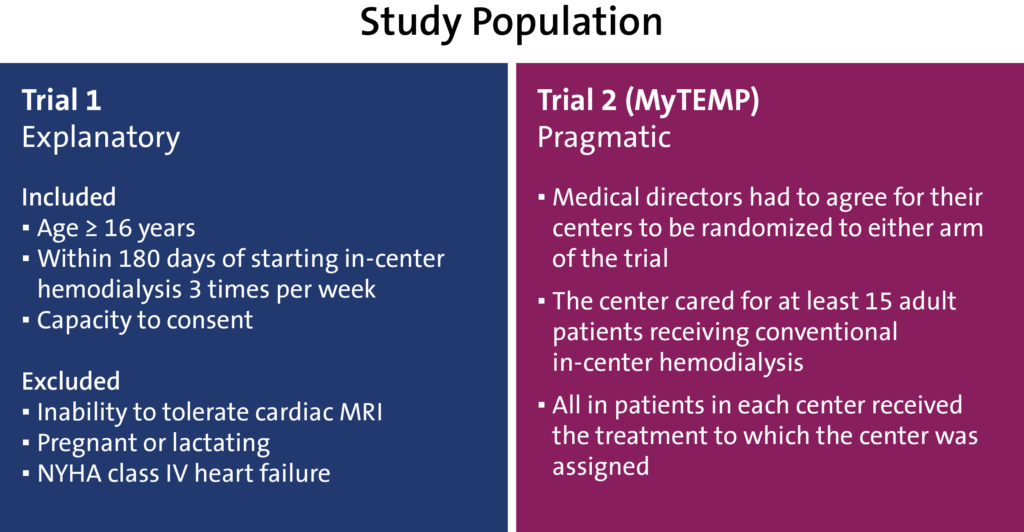
In terms of the trial population, Trial 1 (shaded in blue) was restrictive in its inclusion criteria, having individuals aged 16 years and older who started hemodialysis at the renal clinic setting within the last 180 days and who had the capacity to provide informed consent. In addition, individuals were excluded if they could not tolerate cardiac MRI, were pregnant or lactating, or were classified with New York Heart Association class IV heart failure.
In comparison, Trial 2 (shaded in red) had less restrictive inclusion criteria, which widened its applicability to most usual care providers, patient populations, and settings. For efficiency (that is, ease of trial conduct) and to match the nature of policy on dialysate temperature, which is set by each dialysis center, rather than for individual patients, randomization was at the clinic (or cluster) level. In this design, the medical director of each clinic agreed for their clinic to be randomized to either trial arm, and all patients were part of the trial. A waiver of individual patient consent was sought and granted.
Having a highly pragmatic approach for Trial 2 allowed for the rapid enrollment of clinics and patients (both patients receiving chronic dialysis at the time of randomization and future patients starting dialysis). However, because patients at low and high risk for experiencing the primary outcome were included, a large sample size was required, as nonselectivity reduces the effect size.
Domain: Organization
Trial 1 (shaded in blue) scored low on the PRECIS-2 wheel because the intervention required a specific type of thermometer, trained research staff, a cardiac MRI, and a dialysis machine with the ability to change the dialysis temperature in increments of 0.1 degrees. In comparison, Trial 2 (shaded in red) scored high on the PRECIS-2 wheel because it required no specific expertise or equipment to implement the assigned treatment protocol.
However, because the Trial 2 protocol became the new clinic policy, there was a need to clearly prescribe and set the dialysate temperature. Also, complex roles and social influences on the process of using a personalized dialysate temperature needed to be assessed.
The flowchart below shows the process of who needed to do what differently, the interrelationships between different roles, and the resulting outcomes. In Trial 2, the leadership at each dialysis clinic changed the local policy to ensure alignment with the assigned temperature protocol. Physicians ordered the assigned temperature protocol for current patients at one time and as new patients received prescriptions for dialysate temperature. Nurses were then trained on the trial protocol and asked to follow the physician's orders to set the dialysate temperature. Nurses were also asked to report any issues or adverse clinical symptoms related to dialysate temperature to the treating physician, who could adjust the dialysate temperature as they deemed appropriate.
Domain: Flexibility: Delivery
Trial 1 (shaded in blue) required specific dialysis machines, research nurses, and specific thermometers to implement the study intervention. In comparison, Trial 2 retained the dialysis machines in use at each included center and allowed the dialysate temperature in the intervention arm to be set in the range of 0.5 to 0.9 degrees below the patient's body temperature. Also, the entire trial—at the clinic level—was implemented by clinicians and nurses rather than researchers. Little local research infrastructure was required in the recruiting clinics to implement the trial due to this flexibility.
In the control arm of Trial 1 (shaded in red), the dialysate temperature was set to 37° C. In Trial 2, clinics were instructed to set the dialysate temperature to at least 36.5° C, unless the patient or their nephrologist preferred a different temperature.
Domains: Flexibility: Adherence and Follow-up
As discussed above, Trial 1 (shaded in blue) employed research staff who closely followed patients for the trial duration. There were regular checkups and feedback sessions between the research staff and participants. In comparison, research staff in Trial 2 (shaded in red) had no contact with participants. However, each month, the clinics were asked to randomly select 15 patients and record the dialysate temperature used for a single session. This allowed the study team to estimate the proportion of patients who were “adhering” to the clinic protocol. It should be noted that the level of adherence for Trial 1 was measured at the participant level, whereas adherence in Trial 2 was measured at the dialysis center. level.
Domains: Primary Outcome and Primary Analysis
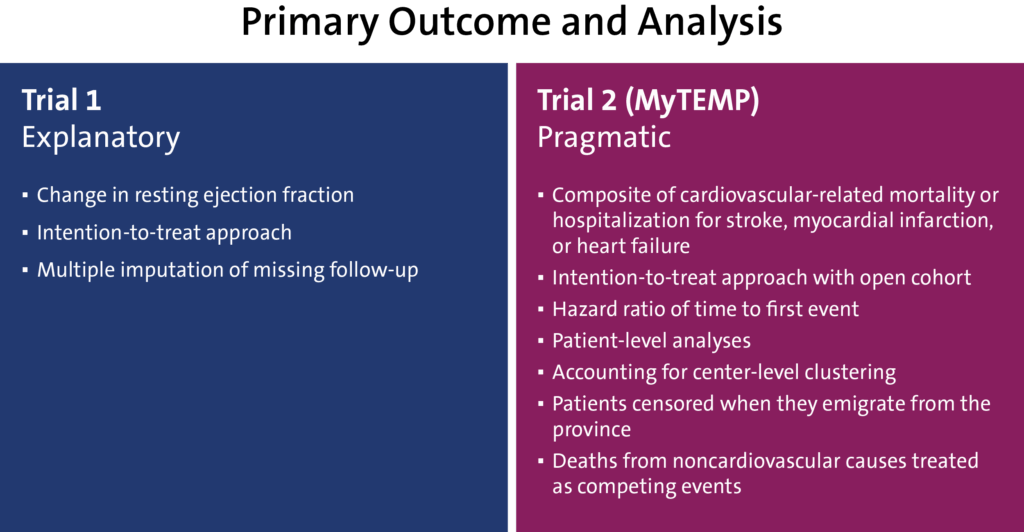
Trial 1 (shaded in blue) had a low PRECIS-2 value (1) for the primary outcome because it tested a change in the resting ejection fraction, which is a surrogate outcome. While important, a change in resting ejection fraction is less relevant to patients. In contrast, for Trial 2, the outcome was cardiovascular-related death or hospital admission for adverse cardiac events, which is of greater relevance to patients and their healthcare providers (PRECIS-2 value 5).
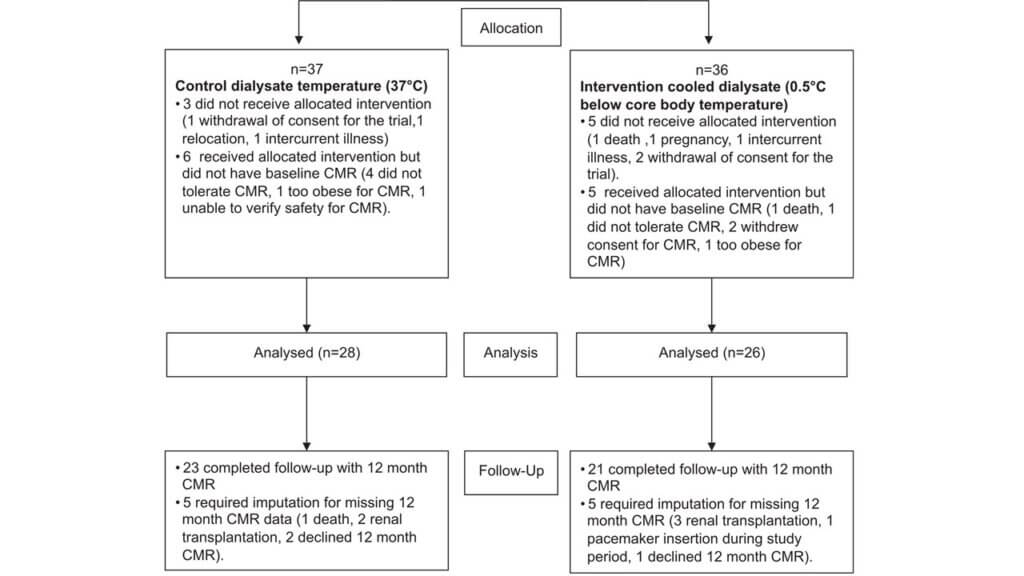
For the analysis domain, Trial 1 used an intention-to-treat approach, which is a highly pragmatic approach. However, nearly 40% of the outcome data was missing due to dropouts or loss to follow-up. From the 73 patients randomized, 37 participants were assigned to the control condition and 36 to the intervention. Of those participants, 28 and 26 were analyzed in the control and intervention arms, respectively. Among those analyzed, data for 5 participants in each arm required multiple imputations for missing outcome data at the 12-month follow-up period.
In contrast, Trial 2 (shaded in red) also used an intention-to-treat approach, but loss to follow-up was expected to be minimal because that typically occurs when study participants leave the (Canadian) province. For example, in Ontario, less than 0.5% the population emigrates from the province each year.
Summary
Pragmatic trials embedded in routine healthcare delivery are increasingly playing a vital role in filling the large gaps in knowledge about caring for patients on hemodialysis. Several fundamental questions in this healthcare setting appear to be particularly suited to pragmatic approaches to trial design. We used Trial 2, the MyTEMP trial, to illustrate a more pragmatic intention, where the authors wanted to test whether the use of a clinic-level protocol of personalized temperature-reduced dialysate results in a different rate of cardiovascular-related deaths or hospitalizations than a standard temperature dialysate. We find it much easier to draw inferences that can be applied to usual care from Trial 2 than we would from Trial 1. The MyTEMP trial was intentionally designed to be highly pragmatic and flexible, which was made possible by:
Frequent and predictable patient encounters
Highly granular and uniform electronic data collection in routine care
Delivery of care by a small number of provider organizations
There is tremendous interest, both nationally and globally, in increasing the momentum for conducting pragmatic trials. Funders of research, including industry sponsors, are increasingly embracing this approach to reduce costs and generate findings that are rapidly translatable to practice.
Trevor Lentz, PT, PhD Tyler Cope, PT, DPT, ACT
Duke Clinical Research Institute
Duke Department of Population Health Sciences
Durham Veterans Administration
Keywords
AIM-Back; Clinical site recruitment; Cluster randomized trial; Low back pain; Recruitment funnel
Key Points
Low back pain is an impactful condition that is more common in the veteran population. Typical low back pain care involves imaging and pharmacologic treatments that don’t always resolve pain issues and may lead to more invasive injection-based or surgical measures that often don’t result in better outcomes.
Research has shown that non-drug treatments (eg, cognitive behavioral therapy [CBT], yoga, physical therapy [PT]) are effective but not often used.
The AIM-Back trial (Improving Veteran Access to Integrated Management of Back Pain), an embedded pragmatic cluster randomized trial, sought to restructure care practices in Veteran’s Administration (VA) healthcare systems to promote and facilitate 2 clinical non-drug pathways that are supported by established guidelines as first-line treatment for low back pain.
Two care pathways were developed in coordination with VA clinicians, veterans, and care givers: (1) Sequenced Care Pathway – This pathway provided an initial onsite physical therapy evaluation and treatment session followed by weekly telehealth physical activity training for 6 weeks. The patient then saw the physical therapist again and was either discharged or provided with 6 weeks of training in psychologically-informed practices to help patients manage pain. (2) Pain Navigator Pathway – In this pathway, a local site clinician who was trained by the study team as a pain navigator discussed and facilitated alternative treatments for low back pain (eg, PT, yoga, CBT, massage). Patient follow up at both 6 and 12 weeks assessed progress and outcomes.
AIM-Back used a novel and intentional recruitment method, borrowing the concept of the business sales funnel, to generate as many site leads as possible. The recruitment process was systematic involving a 3 step framework: (1) Identify leads, (2) Approach leads, (3) Engage and select sites.
In step 1, leads were identified through Warm Market methods (sites known to the researchers), by Leveraging Data (evaluating lists of providers for potential fit), and through traditional Promotional Outreach efforts (advertising through networks and listservs). AIM-Back identified 184 leads from 53 VA healthcare systems.
Step 2 involved approaching leads through email messages. AIM-Back learned that promoting the trial in a way that helps clinicians solve their problems instead of asking clinicians to help with the research was more likely to yield the site. AIM-Back received responses from 23 VA healthcare systems.
In step 3, AIM-Back engaged personnel at all levels, from leadership to clinicians, to assess feasibility and buy-in at the site. AIM-Back selected 19 participant sites within 10 VA healthcare systems.
The Promotional Outreach strategy proved most effective with 9 (47.4%) of sites resulting from this strategy. The Leveraging Data strategy netted 6 (31.6%) sites, and 4 (21.1%) sites came from the Warm Market strategy. Site recruitment took approximately 3.6-3.8 months on average.
17 sites enrolled 1817 Veterans with most sites (n=16) meeting or exceeding the minimum enrollment goal. When sites chose not to participate, they cited a reluctance to change their existing programs, a lack of clinicians or resources, or they were already participating in similar trials.
Discussion Themes
AIM-Back messaging evolved over the course of recruitment from a more traditional trial marketing email to an email that was more personal, short, and leveraged the standing of Duke University. This more personal approach to recruitment led to better relationships with sites during the trial.
Project management software can be helpful for tracking follow up with site leads and communication during the recruitment process.
One overall goal of AIM-Back was to set up a new clinical program that could continue after the end of the trial. Sites were given training materials for the centralized study components and support from AIM-Back was stepped down slowly. Sites that chose to continue the intervention trained a physical activity/whole health coach and a PT for the psychologically informed PT portion of the intervention.
Indicators of a potentially successful site included qualitative components that reflect a high level of engagement such as high interest and excitement in the study along with a sufficient patient population.
Dr. Natalia Morone, principal investigator for OPTIMUM
Trust in their clinicians, positive interactions with study staff, and opportunities for social connection can improve recruitment, retention, and engagement with research participants, according to focus groups of participants in the OPTIMUM trial. These factors can be especially important for first-time research participants and for groups that are historically underrepresented in clinical trials.
The article was published online in Global Advances in Integrative Medicine and Health.
OPTIMUM, an NIH Collaboratory Trial, is studying the addition of mindfulness-based stress reduction to usual care for patients with chronic low back pain, compared with usual care alone, with the goal of improving pain outcomes and reducing opioid prescriptions. Patients in the control group were also offered free mindfulness sessions after the end of the 12-month follow-up period.
Understanding of randomized controlled trials and general research processes emerged as another important theme in the focus groups. In particular, appreciating the value of the control group in a randomized controlled trial can support participants’ ongoing engagement.
“Consistent, positive study staff interactions were particularly important for control group participants who were not immediately receiving the intervention that initially interested them in the trial,” the authors wrote.
The OPTIMUM trial, which is embedded in safety net hospitals and federally qualified health centers, includes a large number of first-time participants in research and patients from racial and ethnic groups that tend to be underrepresented in research. Understanding the needs and perspectives of first-time research participants and those from underrepresented groups can improve recruitment and retention strategies and help ensure the representativeness of study populations.
OPTIMUM is supported within the NIH Pragmatic Trials Collaboratory through the NIH HEAL Initiative by a grant award administered by the National Center for Complementary and Integrative Health. Learn more about OPTIMUM.
Although the need for pragmatic research in primary care settings is great, conduct of pragmatic clinical trials in these settings remains nascent. In a session at the NIH Pragmatic Trials Collaboratory’s 2025 Annual Steering Committee Meeting, Wendy Weber of the National Center for Complementary and Integrative Health (NCCIH) led a discussion about how to expand pragmatic research into primary care settings.
The panelists included Julie Fritz, principal investigator (PI) for BeatPain Utah; Natalia Morone, PI for OPTIMUM; and Sebastian Tong, co-PI for AIM-CP. They shared some of the challenges of conducting research in primary care.
Primary care physicians have multiple competing demands for attention and focus, and a range of topics to cover in a single visit.
The expectation of being offered participation in clinical trials is lower in primary care than in specialty visits.
There are fewer resources that can be diverted to research in primary care, especially time and personnel.
Key Takeaways
How do we adapt pragmatic clinical trials to primary care?
Identify relevant and meaningful research questions
The panelists suggested that, when planning a trial, investigators should think about the primary care setting and consider what problems keep clinicians up at night. Research will be easier to implement if it helps alleviate these problems.
“In primary care, [primary care physicians] are looking at the entire person,” Tong said. “There has to be value added in how we care for the patients with the condition under study, either where the [physician] sees a difference in their patients’ lives or their own lives with respect to reduced burden,” he said.
The panelists also suggested that, for community health centers, there are certain conditions that are linked to data reporting standards, and aligning research with these standards will make studies easier to champion.
Adapt to different kinds of primary care settings
The panelists stressed the need for adaptably and flexibility in intervention delivery because all primary care settings are different. If possible, researchers should tailor the workflow at each site in a way that is familiar to providers. the panelists also suggested that initial engagement by external researchers is best made with someone who is trusted at the site.
Some clinics, including community health centers, may be new to research and may need additional support. Many do not have an institutional review board or a Federalwide Assurance number, and many do not have experience using the electronic health record for research and developing data use agreements.
About the Trials
BeatPain Utah, supported by the National Institute of Nursing Research (NINR), is comparing the effectiveness of nonpharmacologic interventions delivered via telehealth for patients with back pain seeking care in federally qualified health centers in Utah.
OPTIMUM, supported by NCCIH, is assessing the impact of a group-based mindfulness intervention for patients with chronic back pain under usual care circumstances in the primary care setting.
AIM-CP, supported by NINR, is testing the implementation of a care management program to address disparate access to nonpharmacological treatments for chronic pain in rural populations.
A key feature of the NIH Pragmatic Trials Collaboratory is its culture of learning and knowledge sharing among investigators who are planning and conducting pragmatic clinical trials. In a session at the program’s 2025 Annual Steering Committee Meeting, a panel of investigators discussed their recently completed NIH Collaboratory Trials and their thoughts about future directions for pragmatic research.
The panelists included Andrea Cook, co–principal investigator (PI) for BackInAction; Shruti Gohil, lead investigator for INSPIRE; and Stacy Sterling, co-PI for GGC4H. Christine Goertz, a co-PI for IMPACt-LBP, moderated the discussion.
Key Takeaways
What do investigators wish they had known before starting a pragmatic trial? Sterling highlighted a need for ongoing engagement with partnering healthcare systems’ senior leaders to ensure they understand the challenges of adopting and sustaining the study intervention. Cook stressed the importance of educating site personnel about what it means to participate in the trial, including the potential for randomization to a usual care arm.
“We also included nonphysician clinicians in the education about the intervention, because they are often doing the steps being targeted by the intervention,” Gohil added.
How can we apply these lessons in future pragmatic trials? “Doing an embedded pragmatic trial is sort of like having a child: You really need the guidance of people who have gone before you and have real-life experience,” Goertz said.
The panelists proposed the development of more standardized materials for the consent process and other trial elements. They also discussed the need for broader dissemination strategies and new ways to promote implementation tools from trials with successful interventions.
Gohil described her research team’s commitment to developing a dissemination toolkit so people will understand how to approach implementation. She noted that, as soon as the trial was completed but before publication, the research team presented the results to the participating sites.
Greg Simon, the PI for SPOT and a member of the NIH Collaboratory Coordinating Center’s leadership team, stressed the importance of including research partners in dissemination.
“Don’t write the discussion section [of your study results paper] until you’ve talked with your healthcare system partners; they might have something to teach us about what the results mean,” he said.
About the Trials
BackInAction, supported by the National Center for Complementary and Integrative Health (NCCIH), is comparing standard and advanced courses of acupuncture with usual care for older adults with chronic low back pain.
GGC4H, supported by NCCIH, is testing the feasibility and effectiveness of implementing within healthcare systems the Guiding Good Choices program for caregivers of early adolescents to prevent common behavioral problems, such as substance use.
IMPACt-LBP, supported by NCCIH, is evaluating the effect of first-contact patient referral to physical therapists and doctors of chiropractic for low back pain.
INSPIRE, supported by the National Institute of Allergy and Infectious Diseases, used personalized clinical decision support to improve judicious antibiotic prescribing for non–critically ill patients hospitalized with abdominal infections or skin and soft tissue infections.
SPOT, supported by the National Institute of Mental Health, compared care management and dialectical behavior therapy skills training to usual care for adults at risk of self-harm or suicidal behavior.
In a new episode of the NIH Pragmatic Trials Collaboratory Podcast, Rich Platt, Hayden Bosworth, and Greg Simon of the NIH Pragmatic Trials Collaboratory discuss their JAMA Viewpoint, “Making Pragmatic Clinical Trials More Pragmatic.”
In the Viewpoint, the authors propose solutions to the discordance between the results of pragmatic trials and the implementation of those results in healthcare settings.
“I think one of the problems with our evidence generating process is that we may think that our
customers are grant review panels or maybe journal editors,” Platt notes in the podcast. “Those may be our short-term customers, but those are not our ultimate customers. Our ultimate customers are people who have to make decisions about healthcare,” he added.


 The NIH Pragmatic Trials Collaboratory
 Pragmatic clinical trials are conducted as part of routine healthcare delivery and often compare an intervention to usual care. To do this, researchers must understand, monitor, and document standard care at participating research sites.
 At the NIH Pragmatic Trials Collaboratory’s 2025 Annual Steering Committee Meeting, Angelo Volandes, co–principal investigator (PI) of the




 Although the need for pragmatic research in primary care settings is great, conduct of pragmatic clinical trials in these settings remains nascent. In a session at the NIH Pragmatic Trials Collaboratory’s
 A key feature of the NIH Pragmatic Trials Collaboratory is its culture of learning and knowledge sharing among investigators who are planning and conducting pragmatic clinical trials. In a session at the program’s
 In a new episode of the NIH Pragmatic Trials Collaboratory Podcast, Rich Platt, Hayden Bosworth, and Greg Simon of the NIH Pragmatic Trials Collaboratory discuss their JAMA Viewpoint, “Making Pragmatic Clinical Trials More Pragmatic.”